

Understand what your heart cardiovascular testing results really mean
See your biomarkers in context with a comprehensive panel.
- CLIA-certified labs
- HIPAA compliant
- Personalized health protocol
Peripheral artery disease and the plaque biology behind leg pain
Peripheral artery disease biomarkers are blood signals that mirror the biology unfolding inside your leg and body arteries. They spotlight the processes that narrow and stiffen vessels (atherosclerosis) and the risks that travel with them. Broadly, they reflect three themes: irritation and injury of the artery lining (vascular inflammation; examples: high-sensitivity C‑reactive protein, interleukin‑6), burden of artery-clogging particles and metabolic strain (atherogenic lipoproteins; examples: LDL cholesterol, apolipoprotein B, lipoprotein(a), plus glucose control markers such as HbA1c), and a tendency to form clots and lose vessel flexibility (thromboinflammation and endothelial dysfunction; examples: fibrinogen, D‑dimer, von Willebrand factor). Together, these markers help uncover silent artery damage, estimate risk for heart, brain, and limb events, and show whether treatment is calming the disease biology. Kidney stress can add context because it accelerates arterial injury (reduced glomerular filtration). In short, PAD biomarkers translate a complex condition into actionable biology—revealing whether the dominant driver is inflamed plaque, excess atherogenic particles, or a pro‑thrombotic state—and guiding targeted prevention and therapy.
Why a PAD lipid-inflammation panel earns its keep
Peripheral artery disease (PAD) is the downstream result of plaque and inflammation in the arteries that feed the legs—and the same biology affects the heart and brain. Blood tests uncover the drivers of that process: LDL cholesterol (the cholesterol cargo), ApoB (the number of atherogenic particles), Lp(a) (a genetic, pro-plaque, pro-clot lipoprotein), hs-CRP (vascular inflammation), and AIP, the atherogenic index of plasma (a balance of triglycerides to HDL that tracks small, dense LDL).For PAD risk, optimal values cluster toward the low end. LDL is generally “better lower,” often below 100 and, in established atherosclerosis like PAD, typically nearer 70. ApoB is best lower as well, commonly below about 80 and even lower in very high risk. Lp(a) is most protective when low, often under about 30, and risk rises around 50 and above. hs-CRP is lowest-risk under about 1, average 1–3, and high above 3. AIP is desirable below roughly 0.11, intermediate 0.11–0.21, and elevated above 0.21.When these markers are low, the artery wall sees fewer particle entries, less oxidized lipid, and quieter inflammation. That translates to slower plaque growth and fewer limb symptoms like exertional calf tightness. Very low LDL or ApoB can reflect conditions such as hyperthyroidism, malabsorption, or advanced liver disease; symptoms then come from the underlying disorder, not the low number itself. Lp(a) tends to rise in pregnancy and after menopause; having a low Lp(a) at any age is protective. Big picture: these biomarkers integrate lipid transport, coagulation tendency, and immune tone. They interact with glucose control, kidney function, and blood pressure to shape long-term outcomes—claudication, ulcers, heart attack, stroke, and limb loss. Measuring them turns PAD from a leg problem into a whole-system story you can track over time.
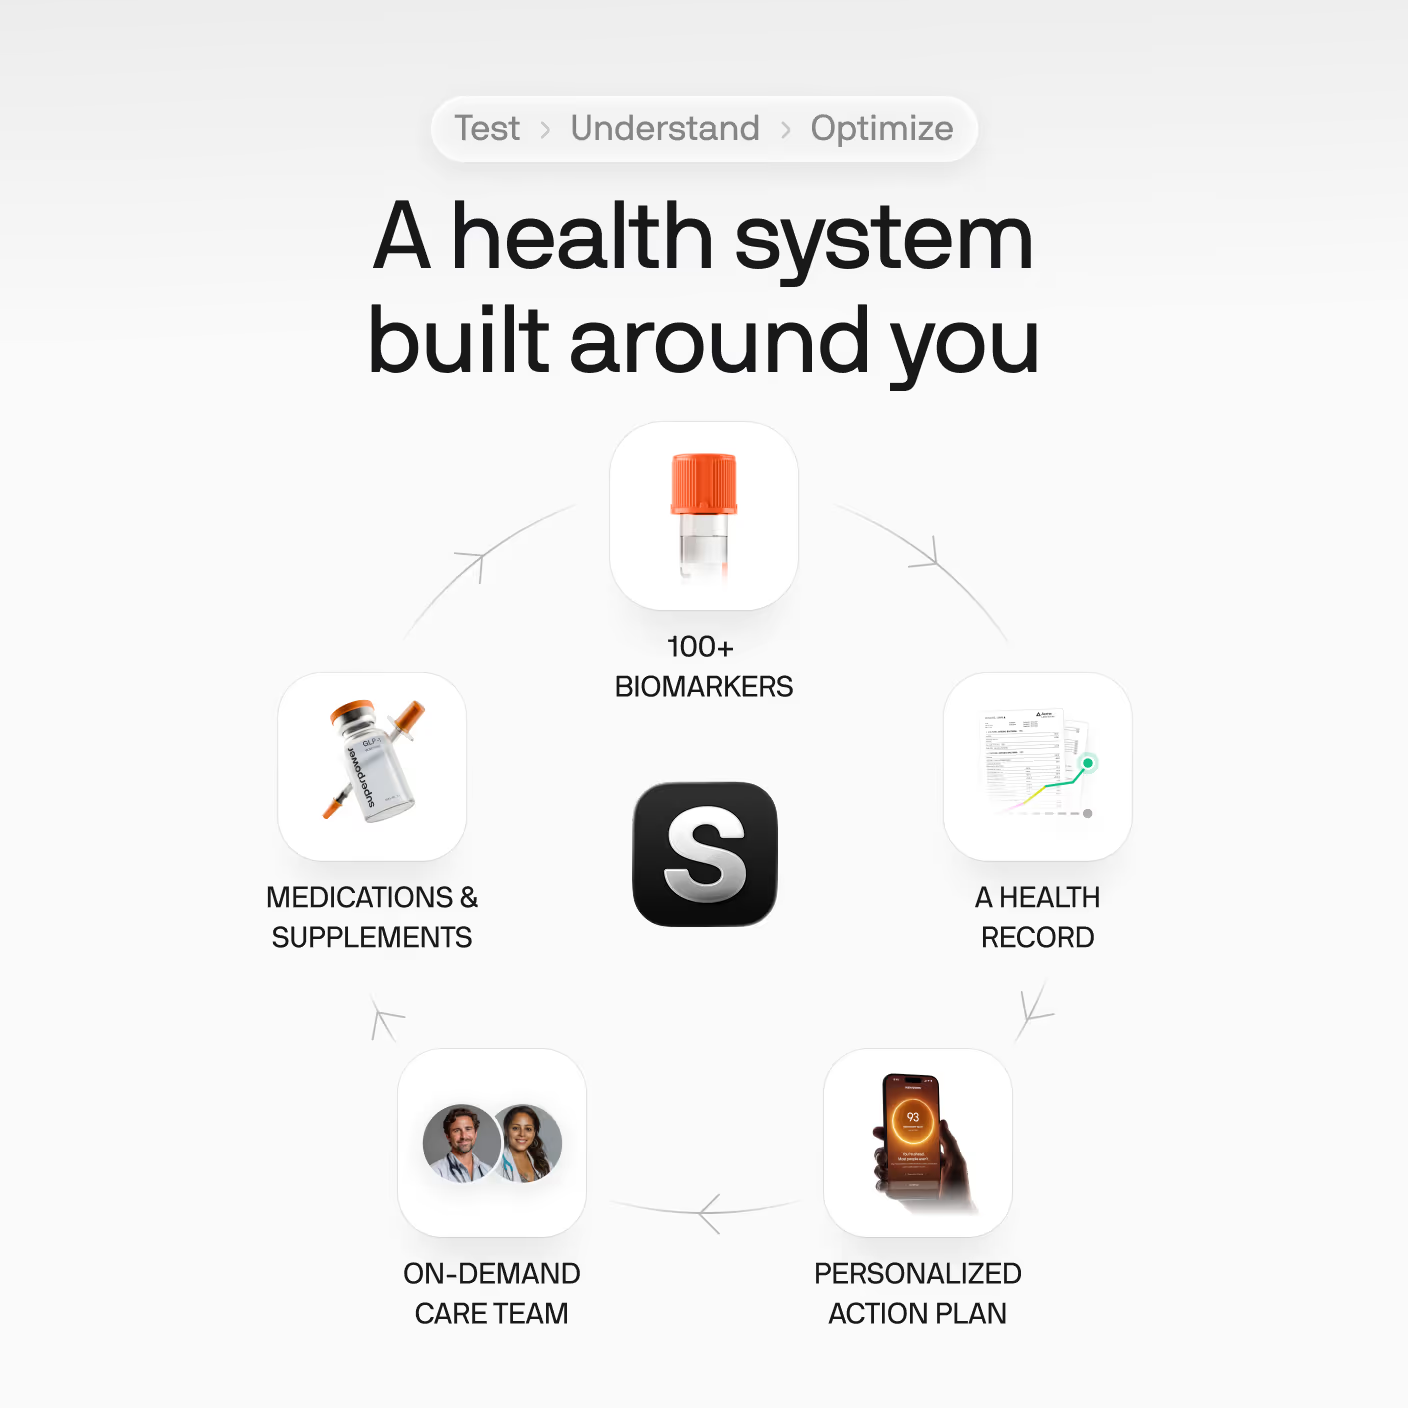
Test 100+ biomarkers
One blood draw. A full picture of your health, explained in plain language.
Test 100+ biomarkers
One blood draw. A full picture of your health, explained in plain language.
The limits of blood tests in PAD
Peripheral artery disease (PAD) blood testing provides a window into the health of your blood vessels and the systems they support, including your heart, brain, muscles, and immune function. PAD occurs when arteries outside the heart and brain—often those supplying the legs—become narrowed by atherosclerosis, reducing blood flow and oxygen delivery. At Superpower, we test LDL cholesterol, ApoB, Lp(a), high-sensitivity C-reactive protein (hs-CRP), and the atherogenic index of plasma (AIP) to assess your risk and vascular health. LDL cholesterol is often called “bad cholesterol” because high levels can contribute to plaque buildup in arteries. ApoB is a protein found on all atherogenic lipoproteins, including LDL, and gives a more precise count of particles that can enter artery walls. Lp(a) is a genetic variant of LDL that is particularly atherogenic and can accelerate plaque formation. hs-CRP is a marker of inflammation, signaling immune system activity that can destabilize plaques. AIP, calculated from triglycerides and HDL cholesterol, reflects the balance between harmful and protective lipids. Healthy levels of these biomarkers suggest stable artery walls and efficient blood flow, supporting energy delivery, muscle function, and cognitive health. Elevated LDL, ApoB, or Lp(a) indicate increased risk for plaque buildup and artery narrowing, while high hs-CRP points to active inflammation that can make plaques more likely to rupture. A high AIP signals an unfavorable lipid balance, further increasing risk. Interpretation of these biomarkers can be influenced by age, acute illness, pregnancy, certain medications, and laboratory methods. These factors may temporarily alter results, so context is important for accurate assessment.
Frequently Asked Questions
References
- Criqui MH, Aboyans V (2015). Epidemiology of peripheral artery disease. *Circulation Research*, *116*(9), 1509-1526. https://doi.org/10.1161/CIRCRESAHA.116.303849
- Kronenberg F, Mora S, Stroes ESG, Ference BA, Arsenault BJ, Berglund L, Dweck MR, Koschinsky M, Lambert G, Mach F, McNeal CJ, Moriarty PM, Natarajan P, Nordestgaard BG, Parhofer KG, Virani SS, von Eckardstein A, Watts GF, Stock JK, ... Catapano AL (2022). Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: A European Atherosclerosis Society consensus statement. *European Heart Journal*, *43*(39), 3925-3946. https://doi.org/10.1093/eurheartj/ehac361
- Ridker PM (2003). Clinical application of C-reactive protein for cardiovascular disease detection and prevention. *Circulation*, *107*(3), 363-369. https://doi.org/10.1161/01.CIR.0000053730.47739.3C
- Sherwani SI, Khan HA, Ekhzaimy A, Masood A, Sakharkar MK (2016). Significance of HbA1c test in diagnosis and prognosis of diabetic patients. *Biomarker Insights*, *11*, 95-104. https://doi.org/10.4137/BMI.S38440
- National Heart, Lung, and Blood Institute. (n.d.). *Peripheral artery disease*. https://www.nhlbi.nih.gov/health/peripheral-artery-disease



















 Heart & Vascular Health
 Metabolic Health
 Energy
 Liver Health
 Kidney
 Sex Hormones
 Thyroid Health
 Nutrients
 Immune System
 Inflammation